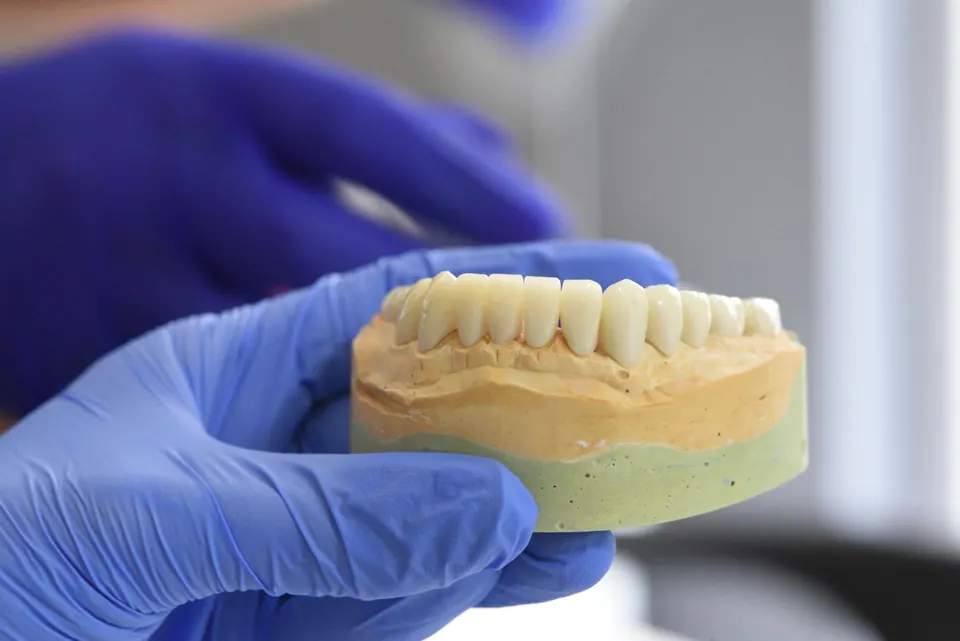
What are the options when you have lost all or nearly all your teeth?
When no teeth remain, or only a few in poor condition, there are four main families of solutions: the conventional complete denture, the implant-retained overdenture (with attachments or a bar), the telescopic prosthesis, which rests on remaining teeth or implants, and the fixed full arch on implants. The right choice depends mainly on bone volume, the teeth still present, how easily you can clean the prosthesis and whether you prefer removable or fixed teeth.
These solutions are not always mutually exclusive: someone may start with a denture, later have it stabilised with implants, or move from a telescopic prosthesis on teeth to one on implants if an abutment tooth is lost.
This article compares the options in practical terms so you can ask the right questions at your consultation.
The conventional complete denture: useful, but with limits
A removable acrylic complete denture rests directly on the gum. In the upper jaw it is held by suction against the palate, often satisfactorily when the bony ridge is well preserved. In the lower jaw it is harder: the supporting area is smaller, the tongue and cheeks move it, and many patients complain of a lower denture that lifts when they speak or eat.
Its advantages are real: no surgery, relatively quick to make, easy to repair and adjust, and good support for the lips and cheeks thanks to the artificial gum.
So are its limits:
- reduced chewing force compared with natural teeth;
- possible sore spots under the denture;
- frequent need for adhesive creams;
- continued bone shrinkage, which means the fitting surface has to be relined regularly.
A well-made denture remains a dignified, suitable solution for many people, especially when surgery is not wanted or not possible.
The removable denture on implants: attachments or a bar
An implant-retained overdenture looks like a denture but clips onto dental implants placed in the bone. It is still taken out every evening for cleaning.
In the lower jaw, two implants are often enough to transform the stability of a lower denture. The McGill consensus statement, published in 2002, proposed this as the minimum standard of care for the toothless lower jaw. In the upper jaw the bone is generally less dense, and more implants are usually planned.
Two main attachment systems are used:
- individual attachments (locator or ball type): a small abutment on each implant snaps into a cap in the denture. Simple and easy to clean; the plastic inserts wear and are replaced periodically;
- a bar: a metal bar connects the implants and the denture clips onto it. It spreads the forces and gives very firm retention, but needs more space and more careful cleaning underneath.
This type of denture often allows the acrylic covering the palate to be reduced, improving taste and comfort.
The telescopic prosthesis: on remaining teeth or on implants
A telescopic prosthesis is based on the double crown principle, rooted in the German prosthodontic tradition. A thin, precisely milled primary crown is fixed on each abutment, whether a natural tooth or an implant. The removable prosthesis holds the secondary crowns, which slide over them with great precision, by friction or a conical fit.
This solution has particular strengths:
- it allows a few healthy remaining teeth to be kept and used as abutments instead of being extracted;
- it can evolve: if an abutment tooth has to be removed one day, the prosthesis can often be modified rather than entirely remade, and an implant can take over;
- it holds firmly while staying removable, which makes cleaning the abutments easier;
- it spreads forces across several supports.
Its constraints: very precise fabrication, several appointments, abutments with healthy gum support and rigorous hygiene around the primary crowns. Our article on the advantages of telescopic prostheses goes into more detail.
The fixed full arch on implants
For people who want teeth that do not come out, a fixed full-arch bridge can be screwed onto several implants, often four to six per jaw depending on the bone available. Only the dentist removes it, at check-ups. All-on-4 and All-on-6 concepts are examples, covered in our article All-on-4 or All-on-6.
The advantages: a feeling close to natural teeth, efficient chewing, nothing to remove and, in the upper jaw, a completely uncovered palate.
The points to assess:
- enough bone in the right places, or grafting beforehand;
- lip support: when a lot of bone has been lost, a fixed bridge does not always replace the volume provided by the artificial gum of a removable denture;
- hygiene: you need to clean under the bridge every day with interdental brushes or a water flosser, which requires some dexterity;
- more extensive surgery and longer treatment.
A fixed full arch is not "the best" solution for everyone: it suits some profiles very well and others less so.
How to choose: the criteria that matter
There is no universal ranking. The choice is built around your situation:
- Remaining teeth: if a few healthy, firmly anchored teeth are left, a telescopic prosthesis puts them to good use. If they are badly affected, keeping them does not always make sense.
- Available bone: a severely shrunken jaw sometimes points towards a removable denture on a few implants, or towards grafting before a fixed solution.
- Facial support: a removable prosthesis with an artificial gum often restores more volume to the lips.
- Maintenance: being able to take the prosthesis out simplifies cleaning, especially with age or if dexterity declines.
- General health: diabetes, smoking, certain bone medications or previous radiotherapy affect whether implants are feasible.
- Your expectations: feeling of fixed teeth, comfort, appearance and the number of appointments you can accept.
Also ask what will happen to the solution in ten or fifteen years: repairability, the possibility of adapting it and expected maintenance. A good proposal considers the future, not just the immediate result.
Maintenance, follow-up and assessment in Agdal
Whatever the solution, follow-up is essential. Removable prostheses are cleaned every day outside the mouth with a dedicated brush, and the abutments, whether implants or teeth, are brushed carefully. Attachments and inserts wear and are replaced; acrylic bases are refitted as the gum changes. Implants need regular checks to prevent inflammation around them.
A few questions to ask at your consultation:
- Can my remaining teeth be used as abutments, or is it better to replace them?
- How many implants would I need, and do I have enough bone?
- Can the prosthesis be adapted if I lose a tooth later?
- What daily care and check-ups should I plan for?
At German Dental Clinic in Agdal, the assessment includes an examination, a digital panoramic X-ray and a discussion of removable and fixed options, including the telescopic prosthesis. If you live in Rabat and your denture no longer satisfies you, you can book an appointment to compare the solutions that suit your mouth.
Frequently asked questions
How many implants are needed to stabilise a denture?
In the lower jaw, two implants often already stabilise a denture considerably. In the upper jaw, where the bone is generally less dense, more are usually planned. The exact number depends on bone quality and volume, the type of attachment chosen and chewing forces, all assessed during the consultation.
Can my current denture be converted to fit on implants?
Sometimes. If the denture is recent, fits well and is in good condition, the attachment caps can in some cases be incorporated once the implants have healed. If it is old, worn or poorly fitting, a new one is generally preferable. The dentist examines it before suggesting either option.
What is the difference between a telescopic prosthesis and a denture on locators?
Both are removable and held by abutments. A locator denture uses standardised attachments screwed onto implants. A telescopic prosthesis relies on custom-milled double crowns that can sit on natural teeth as well as implants. It is more complex to make but allows remaining teeth to be used and can evolve over time.
Should an implant-retained denture be taken out at night?
As a general rule, yes. Taking it out at night lets the gum rest, allows the denture and abutments to be cleaned thoroughly and limits the build-up of bacteria. Your dentist will advise the routine suited to your type of prosthesis, particularly if you grind your teeth or have a specific situation.
Am I too old for implants?
Age alone is not a contraindication. What matters is your general health, bone quality, current medication and ability to look after the prosthesis. For an older person in good health, two implants to stabilise a lower denture often represent moderate surgery that greatly improves everyday comfort.
The information on this page is general. Only a consultation allows a diagnosis and a suitable treatment plan.